Epidermal vs Dermal Hyperpigmentation
Epidermal vs Dermal Hyperpigmentation- searched for as hyperpigmentation, melasma or (in some South African communities) Chubaba, is not a uniform condition, its behavior is dictated entirely by the depth at which the pigment sits. In my experience treating South African skin types, the most common oversight is failing to distinguish between discoloration in the epidermis (the skin’s surface layer) and deposits held within the dermis.
Hyperpigmentation is the broad term for areas of skin that become darker than the surrounding skin. Melasma is a specific, recurring pigmentation condition influenced by factors such as light exposure and hormones. Chubaba is a colloquial term used by some South African communities for facial dark patches; it is not a medical diagnosis and may refer to melasma, post-inflammatory hyperpigmentation or another cause.
This distinction is critical because it directly determines the “stubbornness” of your hyperpigmentation. Our skin produces melanin as a result of a complex biological process called Melanogenesis. This process takes place inside specialized cells called melanocytes, which are located at the basal layer, the very bottom foundation of the epidermis.
Deeper pigment is one reason some dark patches are harder to treat and can take longer to fade. Understanding the skin architecture is the first step to choosing the correct routine and setting realistic expectations for your recovery timeline. That said, you don’t need to study like a doctor. You simply need to understand your skin just enough so that everything finally makes sense and you know exactly what you are dealing with.
Trying to fade stubborn pigmentation? See our Pigmentation, Melasma & Chubaba treatment options →
Table of Contents
The Three-Layer Map of Pigment
To understand your skin, think of it in three distinct sections. Each layer dictates how your pigmentation looks and, more importantly, how we must treat it.
1. Understanding Epidermal Hyperpigmentation: The Surface Layer
This is the surface you see. It is your skin’s “protective shield”. Its main job is to keep the good things in (like water) and the bad things out (like bacteria), and it is constantly renewing itself. That full cycle takes about 28 days.
Epidermal pigmentation is excess pigment located within the epidermis, the outer layer of the skin. It is not simply pigment lying on the surface that can be scrubbed away. This is where common sun spots and post-acne marks live. Because this layer is in a state of constant renewal, shedding old cells and replacing them with new ones, hyperpigmentation at this level is the most responsive to treatment. When you use the correct topical formulas, you are essentially accelerating the removal of these “stained” cells as the skin naturally refreshes itself.
2. The Foundation Layer (The Basal Junction)
This layer sits at the very bottom of your top skin. It is the most important part of the story because this is where your skin’s color is actually created. This layer is also known as the Basal Membrane (or the Dermal-Epidermal Junction). It is like the “security floor” that separates your top skin from the deep layer.
This is where melanogenesis happens. This is where your melanocytes live and breathe. If you don’t address this middle layer, you are only treating the symptoms on the surface without stopping the origin point from overproducing the pigment that creates your hyperpigmentation.
3. The Deep Layer: Understanding the Dermis and Dermal Pigmentation
This is the thick, structural foundation of your skin that sits beneath the middle layer. It contains your collagen, elastin, and blood vessels.
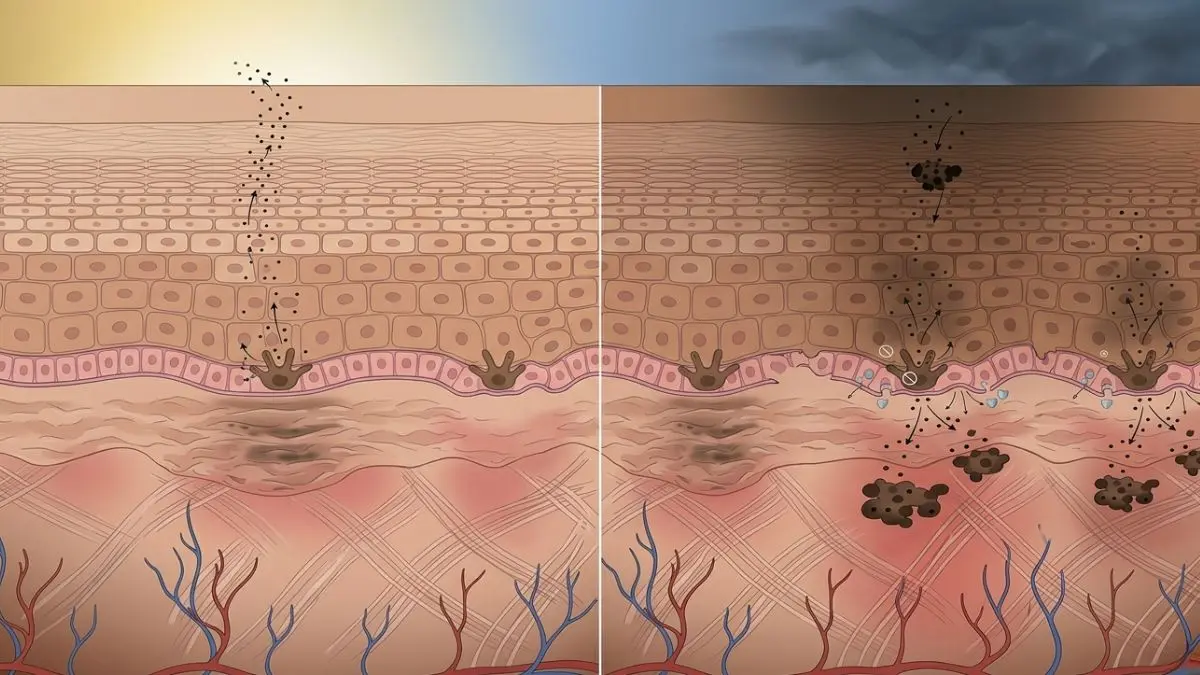
Normally, pigment is created in the middle layer and is transferred upward to the top layer (the epidermis) to eventually be shed away. However, sometimes the pigment can drive downwards instead of upwards. It travels downwards when there is severe inflammation or when the cells in the middle layer become “leaky” or damaged. When the pigment reaches this deep layer, it is called dermal pigmentation.
Pigmentation can also be mixed, with pigment present in both the epidermis and the dermis. Mixed patterns are one reason a dark patch may not respond uniformly or as quickly as expected.
Can You Tell How Deep Your Pigmentation Is Just by Looking?
Not reliably. The colour of a dark patch can give clues, but you cannot confirm pigment depth just by looking in a mirror. A Wood’s lamp may sometimes help a trained professional assess pigmentation, but it cannot always clearly separate epidermal, dermal and mixed pigmentation. This is particularly important in darker skin tones, where Wood’s lamp findings can be less clear.
Melasma is also more than excess melanin. Research has found changes involving the basement membrane, blood vessels and sun-damaged supporting tissue. This helps explain why melasma can be persistent, and why simply trying to ‘bleach’ a dark patch is not a complete treatment strategy.
Epidermal vs Dermal Hyperpigmentation- The Biological Journey of Pigment
Melanin production begins in the melanocytes, which sit at the bottom (Basal) layer of the epidermis. When your skin is triggered, by UV exposure, inflammation, or injury, these cells activate an enzyme called tyrosinase. This enzyme converts the amino acid tyrosine into melanin, the pigment responsible for skin color.
Once produced, the melanin is packaged into tiny structures called melanosomes. These melanosomes are then transferred from the melanocytes into the surrounding cells called keratinocytes. These are the main cells that make up your skin.
From here, the process follows a natural upward pathway. As part of your skin’s normal renewal cycle, these keratinocytes slowly move from the bottom layer up through the epidermis. As they move, they carry the pigment with them toward the surface. Over approximately 28 days, these cells reach the top layer and are eventually shed off. This is how pigmentation is naturally removed from the skin. Skin renewal is gradual, and the time needed for pigmentation to improve varies with the cause, depth, treatment, irritation, light exposure and individual response. A 28-day skin-cycle estimate is not a guaranteed pigmentation-clearing deadline.
The “Leaky” Membrane Reality
However, this system only works properly when the skin is healthy. When there is significant inflammation or damage, the bottom (basal layer) can become compromised.
One histochemical study reported in the Journal of Dermatology (available on PubMed) found signs of basement-membrane damage in 95.5% of melasma samples (Fitzpatrick skin types IV and V) using one staining method. Other studies have reported much lower rates, so this does not mean 95.5% of everyone with melasma has the same finding. When pigment does reach the dermis, immune cells called macrophages may take up the melanin — they are then called melanophages — and this deeper pigment is slower and more difficult to improve.
Instead of melanin moving upward, some of it leaks downward into the dermis. Once pigment enters this deeper layer, it is no longer part of the normal shedding cycle, which is why dermal pigmentation becomes much more persistent and difficult to treat. Because it is “trapped” below the shedding surface, it cannot be scrubbed away or simply lightened with standard surface exfoliants.
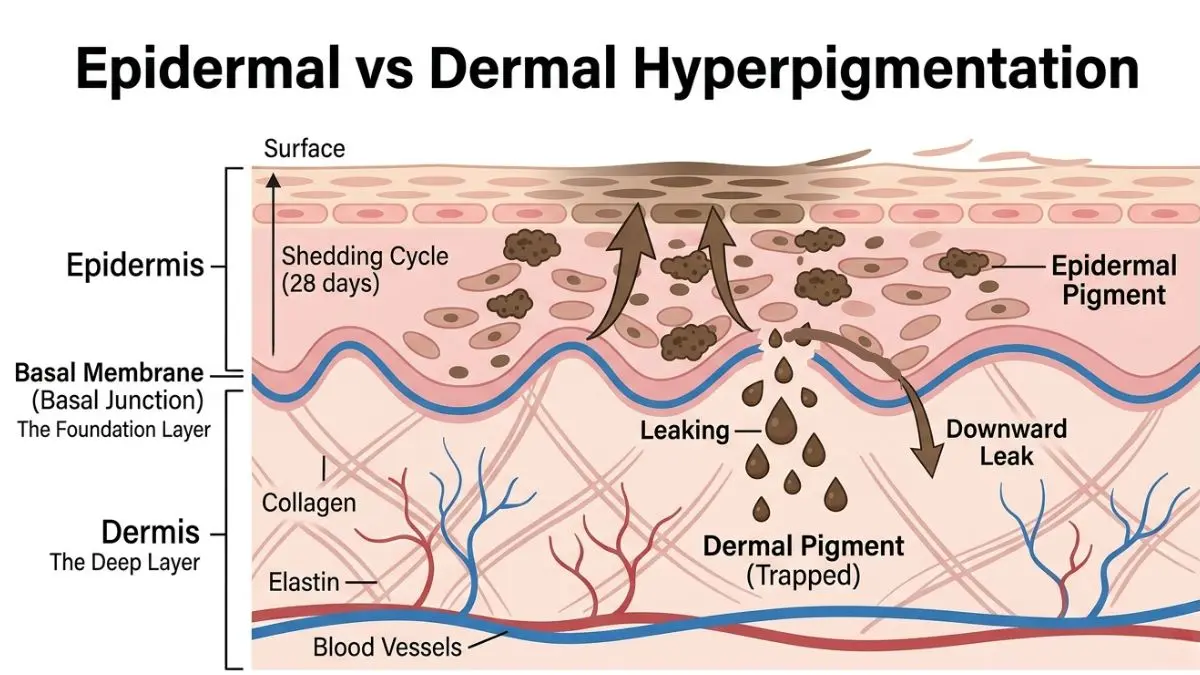 Caption: Epidermal pigment rises naturally with the 28-day shedding cycle, while dermal pigment occurs when melanin “leaks” through the basal membrane and becomes trapped in the deep layer.
Understanding Epidermal vs Dermal Hyperpigmentation is only half the battle. As the clinical data shows, if your basal membrane is “leaky”, your skin is in a state of biological defense. In my manual, “Why is My Melasma or Dark Spots Getting Darker?”, I detail how to identify these invisible inflammation patterns.
Before you move into the 6-Path Strategy below, you must learn to read your skin’s daily signals. My research shows that you cannot treat your skin based on what a bottle says; you must treat it based on what your barrier is telling you. If you skip stabilization and jump straight to aggressive correction, you risk further damage to the Basal Junction and more stubborn hyperpigmentation. You can access my full investigative blueprint by downloading Why is my Melasma or Dark Spots Getting Darker?
The 6-Path Strategy for Epidermal vs Dermal Hyperpigmentation
To address pigment that has “leaked” into the dermis versus pigment sitting on the surface, we have to look at the six biological “checkpoints” in the skin:
1. Tyrosinase Inhibition: This is the “Stop” signal. We must inhibit the enzyme Tyrosinase at the Basal Layer to prevent new melanin from being synthesized.
- The Solution: Our Melanin Breaker targets this factory directly with 4-Butylresorcinol and SymWhite 377.
2. Melanosome Transfer: Even if pigment is made, it has to be “delivered” to your skin cells. We use actives to interrupt this delivery truck so the pigment stays away from the surface.
- The Solution: This is a core function of the multi-active approach in the Melanin Breaker.
3. Antioxidant Defense: Free radicals from intense UV exposure act as “fuel” for your melanocytes. We must neutralize this fuel to keep the factory quiet. We must neutralize this fuel to keep the factory quiet.
- The Solution: The Tetrahexyldecyl Ascorbate (Lipid-Soluble Vitamin C) in our Melanin Breaker provides deep-reaching antioxidant protection that doesn’t wash off.
4. Anti-Inflammatory Stabilization: Since dermal pigment is often caused by a “leaky” basal membrane due to inflammation, we must calm the skin’s “internal heat” to stop the downward leak.
- The Solution: Our Barrier Repair Cream is designed to stabilize the skin and lower the inflammatory “heat” that triggers the leak.
5. Desquamation (Shedding): For the epidermal (surface) pigment, we must support the 28-day shedding cycle to ensure stained cells are moved off the skin’s surface.
- The Solution: While our Pigmentation Exfoliant (Acids) unglues the dead cells on the surface, our Retinoid Firming Cream works from the inside out to speed up the entire 28-day cycle.
6. Structural Barrier Repair: We must seal the skin. A compromised barrier allows external triggers to reach the deeper layers, causing the very inflammation that drives pigment downward into the dermis.
- The Solution: Our Barrier Repair Cream acts as the “Structural Seal”. It calms the internal heat and reinforces the junction between the top and deep skin. This stops the “Downward Leak,” ensuring pigment moves UP to be cleared, rather than DOWN to be trapped.
The Real Truth About Epidermal vs Dermal Hyperpigmentation
The “Real Truth” is that you cannot treat Dermal and Epidermal Hyperpigmentation the same way. One is moving up (and can be cleared), while the other is trapped down (and must be stabilized).
If you treat your skin like a “stain” to be scrubbed, you will only damage the Basal Junction further, leading to more leakage and more stubborn “Chubaba”. Understanding where your pigment lives is the only way to choose a routine that actually works.
Investigate Further: Download: Why is my Melasma or Dark Spots Getting Darker?
Read: Melasma and Hyperpigmentation: Causes, Treatments, and How to Fade Dark Patches
Common Questions: Epidermal vs Dermal Hyperpigmentation
How can I tell if my 'Chubaba' is Epidermal vs Dermal Hyperpigmentation?While a clinical skin analysis is best, epidermal pigment usually appears as well-defined, brown patches that may darken after sun exposure. In contrast, dermal hyperpigmentation often has a fuzzy, bluish-gray or “ashy” cast and sits much deeper in the skin’s architecture, making it appear more “shadowy” than a surface stain.
Why doesn't scrubbing or high-strength exfoliation clear dermal pigment?
Because dermal pigment is “trapped” beneath the Basal Membrane, surface exfoliation cannot reach it. Aggressive scrubbing actually triggers more inflammation, which can further damage the membrane and cause even more pigment to leak downward, making your hyperpigmentation worse.
Does the 28-day shedding cycle affect both types of pigment?
No. The 28-day shedding cycle only moves cells through the Epidermis. Once pigment leaks into the Dermis, it is no longer part of that natural “conveyor belt” and will not be shed away, which is why dermal staining requires stabilized, deep-reaching tyrosinase inhibitors.
Can inflammation cause my surface pigment to become dermal pigment?
Yes. This is the “Leaky Membrane” reality. Severe or chronic inflammation can compromise the junction between your top and deep skin layers. When this “security floor” fails, melanin that should have moved up to be shed instead falls down into the dermis, turning a simple surface spot into stubborn dermal hyperpigmentation.
What is the most important step in the 6-Path Strategy for deep pigment?
The most critical step is Structural Barrier Repair. By sealing the skin and calming the “internal heat” of inflammation, you stop the downward leak at the source. Once the barrier is stabilized, you can then focus on inhibiting the pigment factory and clearing the surface stains.
Explore the pigmentation & melasma guide
Melasma vs HyperpigmentationEpidermal vs Dermal — how deep?You are hereWhy it's getting darkerHow long does it take to fade?
How to remove ChubabaWhat to Use for HyperpigmentationTreatment for dark skinTreat melasma without hydroquinoneDoes microneedling help?
Pigmentation, Melasma & Chubaba SolutionsFind your routine by concernChubaba Dark Patch CorrectorMelanin BreakerGuide: Why is it getting darker?
Best Skin Brightening Ingredients10 actives compared · the hubAlpha Arbutin4-ButylresorcinolKojic Acid DipalmitateMulberry Root Extract